
Last updated: October 22, 2026
Key Takeaways
- Fasting numbers show the overnight baseline, not the meal just eaten.
- Post-meal numbers show how that meal affected glucose.
- A true pattern repeats under similar conditions, at the same test point.
- Share repeated, unclear, or hard-to-explain results with your care team.
If you are trying to make sense of blood sugar readings from a gestational diabetes test, Gestational Diabetes Test Results: How to Read Fasting and Post-Meal Patterns is the key idea: look for patterns, not one number. A single fasting glucose or postprandial glucose reading can look odd for harmless reasons; repeated highs or lows tell a clearer story. Please speak with a qualified professional about your own situation, because pregnancy changes the context fast. For general background, see the American Diabetes Association standards on pregnancy and the NIH/NICHD page on gestational diabetes.
What this page is for, and what it assumes you already have

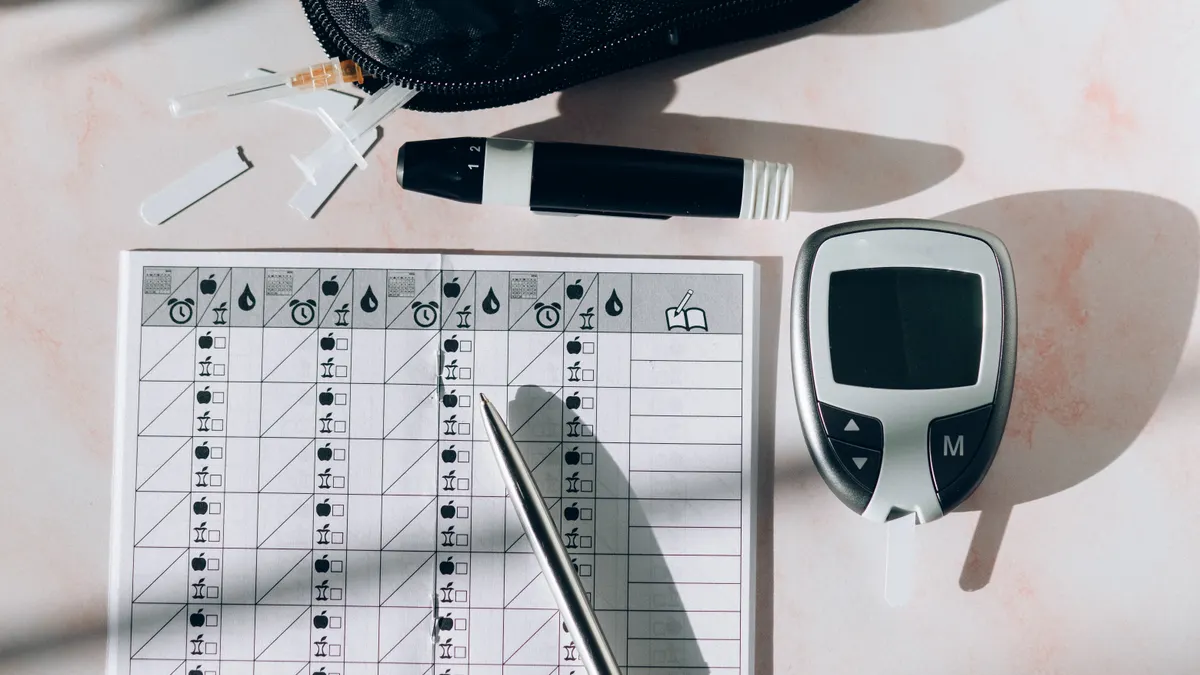
This guide is for someone who already has gestational diabetes test results in front of them — usually a list of fasting glucose and post-meal readings, sometimes paired with a food log — and wants to know what the pattern means. Gestational Diabetes Test Results: How to Read Fasting and Post-Meal Patterns assumes the results were collected in a standard way and that you know which numbers were taken before eating and which were taken after meals. It does not explain how to check blood sugar at home, and it does not set target numbers; those belong on a different page.
The main question here is simpler and more useful: is this a one-off glitch, or does the pattern suggest something your obstetrician should review? That distinction matters because pregnancy is not the place to shrug off repeated abnormalities, but it is also not the place to panic over one strange reading after a skipped meal, a delayed breakfast, or a night of poor sleep.
A readout from 1 day can mislead. A 7-day cluster says more. When results are spread across 1 to 2 weeks, the trend matters more than any single point. I would treat any interpretation as provisional until a qualified clinician has matched the numbers to your meal timing, medications if any, and pregnancy timeline, and you should consult a professional before acting on it.
General searches in PubMed turn up a large literature on gestational diabetes testing, which is one reason the topic is usually handled by pattern rather than by a single number.
Two useful source pages for broader context are the American Diabetes Association’s pregnancy standards and the NIH/NICHD page on gestational diabetes, both of which explain why pregnancy glucose patterns are handled cautiously. See also the CDC’s overview of gestational diabetes and the NIH MedlinePlus page on gestational diabetes for plain-language context.
How to read a fasting glucose pattern
A fasting glucose pattern is the first place I would look, because it reflects the overnight baseline rather than the effect of a meal. In most logs, fasting means the blood sugar was checked after an overnight fast and before the first food or drink of the day, though the exact timing should match the instructions given by the care team.
Start by lining up the fasting values across several days, not just one morning. I would ask four questions of the set: Is the same time point being measured each day? Are the readings clustered, or are they scattered with one outlier? Does the pattern change after a late dinner, a skipped snack, or poor sleep? Is there a run of several mornings that all point in the same direction? That kind of review usually gives more useful information than staring at the highest number alone.
A helpful way to think about it is this: an isolated fasting rise can be noise; a repeated fasting pattern is data. If the same type of reading is high on 3 or 4 mornings in a row, that is more meaningful than one unusual result after an interrupted night. The clinical literature on gestational diabetes testing is broad, which is one reason interpretation tends to stay pattern-based rather than chasing a single number.
Look for the context around each fasting value. A food log can reveal whether the prior evening meal was later than usual, unusually large, or unusually light. It can also show whether the overnight window was truly long enough to count as fasting. If the pattern shows only one abnormal fasting result after an atypical evening, that is a different signal from a repeating morning rise with no obvious trigger. The first suggests an isolated fluctuation; the second suggests a trend worth showing your obstetrician.
What post-meal readings tell you that fasting numbers do not

Postprandial glucose — the blood sugar measured after a meal — shows how the body handled the meal just eaten, not the overnight baseline. That makes it the better lens for meal-related spikes, and the less useful lens for judging fasting status. The term itself is technical, but the idea is simple: compare what happened after breakfast, lunch, or dinner, not just whether one number was “good” or “bad.”
The most useful habit is to compare the same meal slot across days. A breakfast pattern that rises after cereal but not after eggs tells a different story from a lunch pattern that is consistently higher regardless of what was eaten. A one-time spike after a dessert or an unusually large portion may be an outlier. A repeated rise after the same meal slot is a pattern. That is where a food log earns its keep, because it helps separate the meal from the meter reading.
Timing matters here. A reading taken at the instructed post-meal interval is easier to interpret than one taken early or late. A number drawn 15 minutes before the intended mark can miss the peak; a number taken much later can look reassuring even if the meal caused a short spike that already passed. That does not make the reading useless, but it does make it less comparable to the rest of the log.
I would also watch the shape of the day. If fasting values look stable and only one meal period shows repeated elevations, the issue may be meal-specific rather than global. If all three post-meal periods are repeatedly elevated, the pattern is broader. That does not tell a person what to change, but it does tell a clinician what to review. Studies in this area are still weighted toward summaries and clinical reviews; the median publication year in the 100-record sample was 2020, and the median study duration figure reported in these abstracts was 26 weeks, which suggests that interpretation is usually built from trends over time rather than a one-day snapshot.
How do you tell a one-off reading from a real pattern?
A real pattern repeats in the same direction, at the same measurement point, under similar conditions. A one-off reading does not. That distinction sounds obvious, but it is the part people miss when they open a glucose log and fixate on the highest number.
I would use a simple rule: one odd result is a note; repeated odd results are a message. If a single fasting value is out of line after a poor night of sleep, a late dinner, or an illness, that is not the same as several fasting values that trend upward over a week. If one post-meal value rises after a very large or very carb-heavy meal, that is not the same as repeated post-meal rises after ordinary meals at similar times of day.
The other question is whether the pattern is consistent enough to trust. A cluster over 3 to 7 days is more informative than two scattered numbers separated by a long gap. A food log helps here because it shows whether the readings came after the same meal composition, at the same interval, and in the same part of the day. If the log is incomplete, the pattern is harder to interpret and easier to overread.
I would be especially cautious about drawing conclusions from a short run with missing context. A log with 4 readings, one skipped dinner entry, and one late-night snack entry can look more alarming than it is. On the other hand, if the same type of reading is repeatedly off even when meals and timing look ordinary, that is the kind of trend an obstetrician should see sooner rather than later.
This is also where the field’s evidence base matters: the PubMed sample included only a small number of meta-analyses and systematic reviews, so pattern interpretation still depends heavily on clinical context, not on a single pooled answer.
What should you share with your obstetrician?
You should share anything that looks repeated, unclear, or hard to explain from the meal log. In practice, that means a run of several fasting glucose results that point the same way, repeated postprandial glucose elevations after the same meal slot, or a log full of readings that cannot be matched to meals, sleep, or timing. If you are unsure whether a pattern matters, send the log anyway; ambiguity is part of the point.
Bring the numbers with context, not just a pile of values. A clean handoff includes the date, the time of each reading, whether it was fasting or after a meal, what was eaten before the post-meal reading, and whether anything unusual happened the night before. If there is a food log, include it. A pattern with no context can be hard to act on; a pattern with context can often be interpreted much faster.
I would not wait for a dramatic outlier if the trend is already repeating. A gradual drift in fasting numbers over several mornings can matter more than a single higher spike, because trends can hide in plain sight. The same is true for a post-meal series that stays mildly elevated after multiple meals rather than leaping high once. The reason is practical: recurring patterns help a clinician decide whether the log needs closer review, more structured monitoring, or simply a check on timing and technique.
This is also where the limits of self-interpretation show up. Blood sugar readings in pregnancy are not a stand-alone scorecard. They are one part of a larger picture that includes gestational age, meal timing, symptoms, and the rest of the prenatal record. A qualified professional can place the numbers in that context more safely than a chart can. For related context, see the ACOG patient guidance on gestational diabetes and the American Diabetes Association’s pregnancy standards.
When a reading pattern should not be brushed off
A repeated pattern should not be brushed off when it stops looking random. In pregnancy, that is the point at which I would stop trying to explain it away with one unusual meal or one rough night and start treating it as information to pass on; please consult a professional if the pattern keeps showing up. The question is not whether the pattern is dramatic; it is whether it keeps appearing.
Several fasting values rise on different mornings: This suggests a recurring overnight pattern, not a one-time blip — share the log with your obstetrician and include the timing of the previous evening meal.
Post-meal values keep rising after the same meal slot: This points to a repeatable meal-related pattern — bring the food log and the time interval used for each reading.
The readings are all over the place and the timing is inconsistent: This makes the log hard to interpret — ask for help reviewing timing before reading too much into the numbers.
Only one value is odd, and the rest look stable: This is more likely an outlier than a trend — note it, but do not let it outweigh the rest of the series.
Meal entries are missing from the food log: Missing context weakens the whole pattern — fill in what you can and show the incomplete log anyway.
I would also treat changing patterns cautiously if the readings shift after a major change in schedule, sleep, illness, or meal timing. Those changes can alter the meaning of the log even when the numbers themselves look similar. That is one reason a clinician will often ask for several days of readings rather than relying on a single 24-hour slice.
Common mistakes that distort the picture
The biggest mistake is treating one number as the whole story. A lone spike can be unsettling, but a whole week of readings tells the better story. The correction is to compare like with like: fasting with fasting, the same meal slot with the same meal slot, and one day with several days.
A second mistake is mixing up the labels. If fasting and post-meal readings are not clearly marked, the pattern becomes muddy fast. The correction is to keep each reading attached to its time point and meal context so the trend is readable at a glance.
A third mistake is ignoring the food log. Without it, the reader sees numbers but not the conditions that produced them. The consequence is overinterpretation; the alternative is to keep even a brief log of meal timing and meal content so the readings have context.
A fourth mistake is assuming that a normal-looking post-meal number erases an abnormal fasting pattern, or vice versa. Those are different signals. The correction is to review them separately before deciding whether the overall pattern is stable.
A fifth mistake is waiting too long because the numbers are “only a little off.” Small repeated deviations can still matter when they keep showing up. The right response is not panic; it is to share the trend with a qualified professional before the log runs for another week with the same issue.
A sixth mistake is trying to use a generic online chart as if it could replace the prenatal plan already given. It cannot. Gestational diabetes monitoring is individualized, and the right interpretation depends on the person, the pregnancy, and the instructions already in place.
What changes the interpretation?
The standard reading pattern needs adjustment when the context changes. A missed meal, an unusually late dinner, a night shift, vomiting, illness, or a big change in routine can all shift the meaning of a fasting or post-meal result. In those cases, the same number may not mean the same thing it meant on a normal day.
Pregnancy timing also matters. Patterns earlier in pregnancy may be viewed differently from patterns later on, because the metabolic load changes as pregnancy progresses. That does not mean one stage is easy to ignore; it means the same log may be interpreted differently at different points in time.
A food log becomes especially useful when meals are unusual. If the diet on one day looks nothing like the rest of the week, that day should not be weighted the same way as the others. Likewise, if the log shows several days with poor sleep or delayed meals, the pattern may reflect schedule stress as much as meal composition.
There is one more edge case: if the readings are being gathered under a different protocol from the one originally discussed, the pattern may not be directly comparable. That is a setup problem, not a personal failing. It is worth clarifying with the obstetrician before reading too much into it.
For broader monitoring context, the hub on gestational diabetes testing and monitoring can help place these results in a wider care plan.
Drafted with AI; not yet reviewed by a person.
